

Temp vs Full-Time Dental Hire: Making the Choice
By Dr. Brian Passell and the DDS Recruit team ·

Summary: The decision between temporary and full-time dental hires depends on whether the practice faces a short-term scheduling issue or requires a permanent role for patient continuity, production planning, and team culture. Temporary coverage suits defined gaps, while a long-term hire is essential for carrying patient relationships and supporting the practice's growth and stability.
A hygienist texts that she will be out for the week. The associate candidate you liked takes another offer before the owner can approve terms. Meanwhile the schedule still has hygiene checks, treatment plans, and handoffs, and none of that stops while the practice sorts out whether the opening is brief or permanent.
The choice between temp coverage and a full-time dental hire is not really about which one feels safer. It turns on whether the practice has a short scheduling problem or a role the business has to own for patient continuity, production planning, and team culture.
A locum or temporary clinician keeps chairs moving when the need has a clear finish line. A long-term hire is a different kind of work. The practice is choosing who will carry relationships, lead standards, and stay through the next phase of growth. Mix up those jobs and offices spend too much on temporary coverage, or they rush into a hire that should have been handled as a longer search.
Temporary dental staffing: best for a defined gap
Temporary dental staffing works when the vacancy has a clear edge, like a leave, a delayed start date, an unexpected resignation, or a hygiene schedule that needs coverage while the practice keeps recruiting. The point is continuity, not reinvention, because a temp clinician is there to protect today's schedule rather than become the clinical future of the office. A locum dentist makes the most sense when the practice already knows the gap will end, or when patient demand is too immediate to wait for a permanent associate search. Hire locum dentists instead of associates when the role is coverage for a known period, when the owner doctor will keep clinical leadership, or when the practice has not yet shown that patient flow supports another permanent provider.
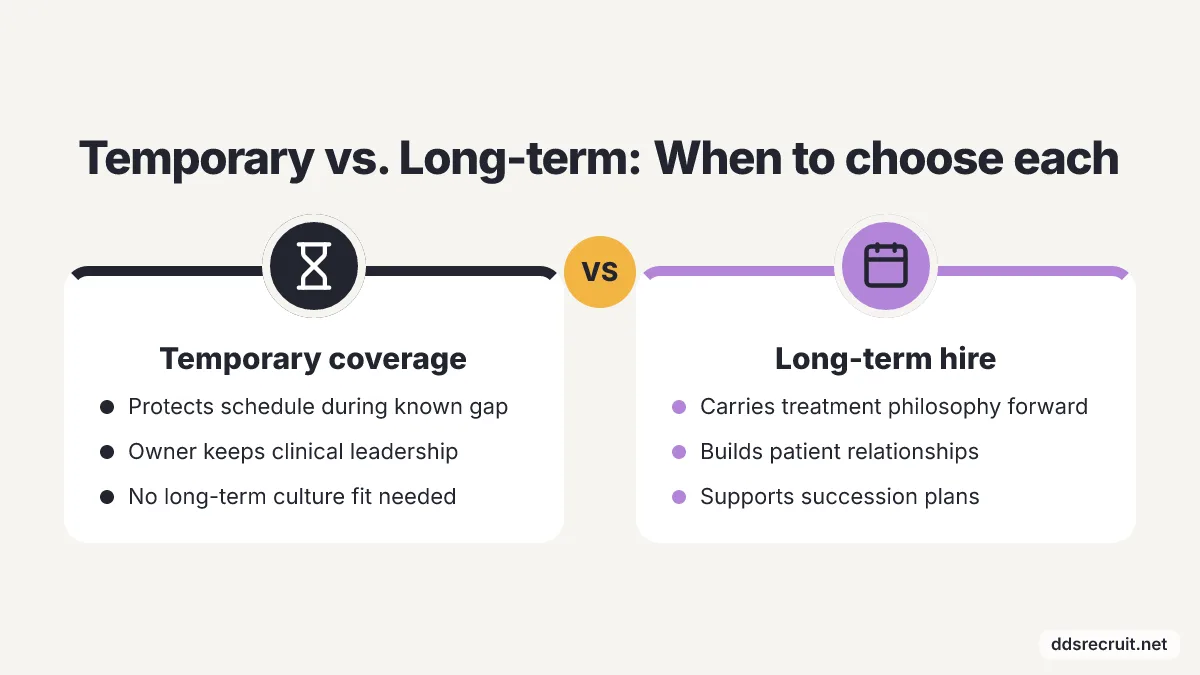
Temporary coverage also buys time when a rushed full-time hire would create more risk than relief. DentistryIQ's 2023 poll found that more than 60% cited staffing and recruitment as a leading concern, which means the pressure to "just fill the chair" is not only a small-office problem. A temp role gives the practice room to keep operating while the owner sorts out an emergency from a durable headcount decision. Temporary staffing has real limits. A short-term clinician may not be the person to carry a multi-year treatment philosophy, mentor assistants, build specialty referrals, or represent the practice in a succession plan. If the office keeps renewing coverage because the owner does not have time to define the permanent role, the temp solution has turned into a stand-in for leadership work instead of a staffing tool.
The named exception is a practice testing demand for a new provider. A single-location office adding clinical days after a marketing push should not treat early schedule pressure as proof that a full-time associate is needed, because temporary or part-time coverage can test whether patient flow repeats after the first wave of demand. Once the schedule, case mix, and owner expectations are clear, the practice can decide whether to open a long-term search.
Temporary staffing is the stronger choice when the practice can name the end point and the work to be covered. If the same problem keeps coming back after each short-term placement, the vacancy is no longer temporary, and the next decision belongs in a permanent hiring plan.
Long-term associate and doctor hiring: best for ownership of care
A long-term associate or doctor hire makes sense when a practice needs someone who will keep patient relationships intact, keep treatment planning steady, and help with future capacity. The hire reaches far past next week's calendar. Patients adjust, assistants adjust, and the front desk starts working around that clinician's habits and availability.
The long-term decision should begin with the role the practice actually needs. An associate dentist who will take overflow is a different hire from a doctor expected to add procedures, support a second location, or move toward eventual ownership transition. If a practice skips that definition before recruiting, it sets itself up for a mismatch between the candidate's career plans and the owner's business plan.
Culture fit matters more in a permanent dental hire than it does in a pure coverage situation. A clinician can have the right license, procedure mix, and schedule, and still be the wrong person for a private PPO-based office where the owner wants careful handoffs, steady team rhythms, and a particular patient experience. The useful question is not whether the dentist can do the dentistry. It is whether the dentist fits inside this practice after the first burst of relief wears off. ADA News reported in 2025 that 62% of dentists named staffing shortages as their top challenge for 2025, so waiting for a perfect applicant pool is not a plan. A better long-term move is to make the role concrete enough that the right candidates can see the opportunity, and the wrong candidates can rule themselves out before the practice spends more time.
DDS Recruit is a fractional, culture-first dental recruiting team backed by 17 years of dentistry-only search experience that matches for fit, not just résumés. Its work includes dental associate and doctor recruiting, specialist and in-house specialist placement, and C-level executive search for roles such as Chief Clinical Officer and COO.
A long-term search also changes the economics of the decision. Those terms do not make every permanent search the right answer, but they do address the owner's fear that a wrong permanent hire leaves the practice paying twice.
Job postings show how specific long-term opportunities become once a practice commits to a real role.
A long-term associate or doctor hire is the better path when the practice is hiring for continuity, production planning, and team fit. If the need is only to keep the schedule open during a narrow disruption, the permanent search can run in parallel without pretending the temp clinician and the future doctor are the same decision.
Specialist, hygienist and office manager hiring: best when the gap changes the model
Specialist, hygienist and office manager hires belong in a different bucket from emergency coverage, because each role can change how the practice runs. An in-house specialist shifts referral patterns and case acceptance. A hygienist changes recall capacity. An office manager affects the daily pace of both the front desk and the clinical team.
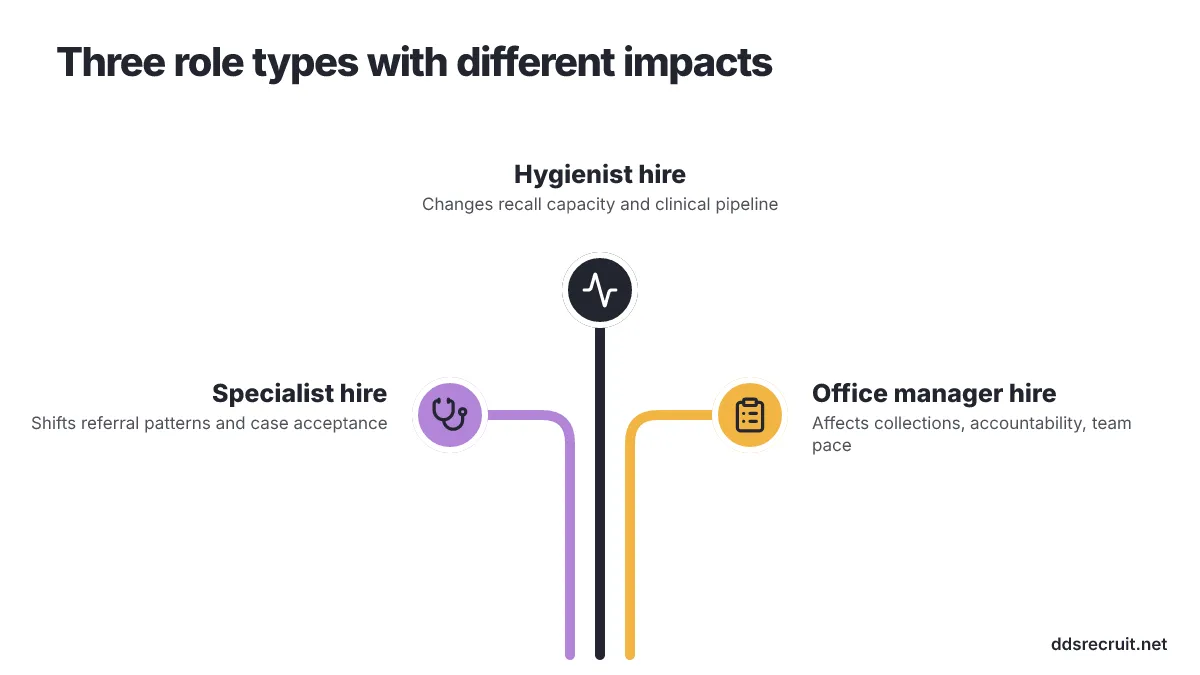
A temporary hygienist can keep a recall column from falling apart during an absence. Long-term hiring starts when hygiene capacity is the choke point for diagnosis, perio maintenance, and patient retention. ADA News reported in 2025 that hygienist-hiring difficulty stayed high, with about 90% calling it challenging even after it eased from earlier pandemic levels. When a practice keeps losing hygiene days, it is not just short-staffed. It is also shrinking the clinical pipeline that supports restorative care. Specialist hiring needs a firmer business case than short-term doctor coverage. An in-house endodontist, periodontist, oral surgeon, or orthodontic provider needs a referral base, treatment rooms, equipment assumptions, and scheduling support that a general associate may not need in the same way. If the practice has not matched the provider's skills to patient demand and internal referral behavior, the wrong hire can sit idle.
Office manager and key team member hiring creates another situation where temporary coverage can hide the real problem. A front-desk temp can answer phones and keep check-in moving. A permanent office manager is tied to collections discipline, team accountability, schedule control, and owner communication. A rushed manager hire causes a different kind of damage than a missed clinical day, because one person can reset office norms before the owner realizes the fit is wrong.
A practice comparing temporary help with permanent hiring should not treat every vacancy as the same job class. A clinical coverage gap and a leadership gap carry different risks.
Related dental businesses can sit around the hiring decision without replacing it.
The trade-off is cost and attention. A permanent specialist, hygienist, or manager search asks the owner to define the role more carefully than a temp request, and that work takes time away from day-to-day production. Temporary coverage still helps while that work is happening, but it should not decide the long-term shape of the practice by default.
DSO expansion and succession roles: best when hiring carries leadership risk
DSO expansion lead placement and succession planning hires are not coverage problems, even when the vacancy feels urgent. A leader hired for expansion, transition or executive oversight affects acquisition pace, clinical consistency and whether local teams trust the next stage of the business.

Group and DSO leaders face a different version of the temp-versus-permanent decision. A location may need temporary clinical coverage immediately, but the organization may also need a Chief Clinical Officer, COO, expansion lead or successor doctor who can carry decisions across multiple offices. Treating those roles like job-board openings creates a mismatch between the importance of the role and the seriousness of the search.
Becker's Dental Review reported in 2024 that the United States had 6,861 federally designated dental shortage areas needing 9,938 more dental professionals. Becker's Dental Review also cited a McKinsey projection of a 36,000-professional dental shortfall by 2031. Expansion hiring happens inside that supply environment, which means the strongest groups cannot rely on volume-based outreach alone.
A DSO expansion lead is a long-term hire because the person is connected to market selection, integration judgment and the ability to translate strategy into local execution. A temporary operator can support a project, but a true expansion lead becomes part of how the organization chooses opportunities and absorbs new practices. That distinction changes both the search and the interview standard.
Succession planning has the same problem in a smaller frame. A retiring owner may need temporary provider coverage during the transition, but the successor hire must be credible to patients, staff and referral partners. The wrong successor is not simply a bad hire, because the practice's goodwill may leave with the departing doctor if the transition feels unstable.
The question for a growing group is whether the open seat is a production seat, a leadership seat or a transition seat, because each one carries a different failure mode.
A separate relationship channel can matter for candidates and recruiters working around these searches.
Leadership and succession hires justify a longer search when the person will shape the business after the vacancy is filled. Temporary coverage can keep locations open during that search, but it should not be mistaken for the solution to a leadership vacancy.
How should a practice choose?
The first thing to weigh is the cost of getting it wrong. Losing a week of hygiene hurts. Putting the wrong associate, specialist, office manager, or expansion leader in place can damage patient trust, shake team morale, and eat up owner bandwidth long after the vacancy itself has passed.

| Staffing path | Best fit | Main advantage | Main trade-off |
|---|---|---|---|
| Temporary dentist or hygienist | A bounded absence, delayed start or demand test | Keeps the schedule moving while the practice decides | Does not solve culture fit or long-term leadership |
| Long-term associate or doctor hire | A durable provider role tied to patient relationships | Builds continuity around care and capacity | Needs a clearer role definition before recruiting |
| Specialist or in-house specialist hire | A practice adding procedures or keeping referrals inside | Ties hiring to a clinical growth model | Needs proof that patient demand and scheduling support the role |
| Office manager or key team member hire | A business rhythm or accountability gap | Changes how the practice runs day to day | A poor fit can spread across the team quickly |
| DSO expansion or succession hire | Multi-location growth, transition or executive need | Carries decisions beyond one operatory | Takes more owner or leadership attention to define |
Temporary coverage makes sense when the schedule problem is immediate and bounded. A long-term search fits when the role will shape care standards, patient relationships, leadership continuity, or growth plans after the immediate vacancy is gone.
The first step is to write the vacancy in one sentence without using a job title. We need someone to cover hygiene for a leave points toward temp coverage. We need a doctor who can expand restorative capacity and stay aligned with the owner's patient philosophy points toward a long-term associate search. If the sentence mentions acquisition, transition, multi-location leadership, or executive oversight, the role has moved beyond simple clinical coverage.
The second step is to separate patient schedule risk from hiring risk. Schedule risk asks what happens if nobody is in the chair next week. Hiring risk asks what happens if the wrong person joins the team for the next stage of the practice. A practice with high schedule risk and high hiring risk may need both answers at once, temporary coverage now and a permanent search that is not rushed by panic.
The third step is to decide who must own the search. A small office may handle a short temp request internally if the need is simple. A long-term clinical or leadership hire adds candidate fit, compensation expectations, and practice positioning to the owner's workload.
The fourth step is to ask what would make the hire fail. For a temp dentist, failure may be poor coverage of the planned schedule. For a permanent associate, failure may be a mismatch with the owner's clinical style or the candidate's career goals. For a C-level or expansion hire, failure may be a leader who looks qualified on paper but does not fit the group's operating reality.
A practice that cannot answer those questions should not default to the most available candidate. The safer move is to use temporary staffing for the immediate schedule need, then define the permanent role before spending owner time and candidate goodwill on a search that is not ready.
Conclusion
Start by naming the vacancy without the job title, then decide whether the office needs coverage, continuity, or leadership. That single sentence will tell the practice whether to call for temporary help, open a long-term associate search, or scope a specialist, manager, expansion, or succession role.
The work takes honest role definition and enough patience not to let a full schedule make the decision by itself. Temporary staffing protects the week in front of you. Long-term hiring asks who should carry the practice after the immediate pressure passes, and that is where the advice stops: once the role affects ownership, culture, or growth, the practice needs a search conversation rather than another stopgap.