

Dental Associate Placement Built for Long-Term Fit
By Dr. Brian Passell and the DDS Recruit team ·

Summary: Dental associate placement built for long-term fit starts with the associate role itself: the patient base, the pace of the schedule, the owner's case presentation style and any transition path. A résumé shows eligibility, not whether an associate will practise the way the office does, so settle those points with the candidate before an offer.
The usual advice says to hire the dentist with the strongest résumé, clean credentials, and the biggest production history. That advice falls apart when a private practice, or a growing group, needs an associate who will stay, treat patients the way the office already does, and work within the team rhythm already there. Associate hiring is not the same thing as filling a shift. Dental associate placement that aims for long-term fit starts with the actual job the dentist is stepping into: the patient base, the pace of the schedule, the owner's clinical philosophy, the handoff with hygienists, and the future path inside the practice.
Long-term fit should come before résumé depth in dental associate and doctor recruiting. A résumé can show eligibility, but it cannot tell an owner whether the doctor will accept the practice's case presentation style, communicate well with the front desk, or grow into a transition plan without friction.
Why the résumé breaks down in dental associate hiring
A résumé answers the easiest question first, whether the candidate looks qualified on paper. Dental practices still need that baseline. Paper qualifications do not show how a doctor responds when a patient declines treatment, when a hygienist raises periodontal concerns, or when the owner wants the same diagnosis and documentation every time. Production history can help, but those numbers need context before they shape a hiring decision. A dentist who produced heavily in a fee-for-service setting may have trouble in a PPO-based suburban office if the treatment mix, appointment lengths, support team, or patient expectations are very different from the prior role.
Job boards create another kind of distortion because they reward speed and volume. DDS Recruit places its work against generic job boards and volume-based recruiters by focusing on fit rather than only résumés, according to its culture-first recruiting team positioning. That difference matters when the wrong hire affects chair time, team morale, and patient continuity.
Hiring dental associates beyond résumé screening means treating the résumé as a filter, not the decision. The better question is whether the dentist can do this work, with this team, for this patient base, under this owner's expectations.
Short-term coverage is the named exception. When a practice needs temporary relief for a leave, a vacation gap, or a narrow clinical backlog, availability and credential fit can outrank deeper culture assessment because the role is not meant to become part of the practice's future.
What an associate role should spell out before an offer
Culture fit should be defined as observable working alignment, not personality similarity. A practice owner does not need an associate who thinks exactly like the owner; the practice needs a dentist whose clinical judgment, communication habits, schedule tolerance, and growth goals can operate inside the office without constant correction.
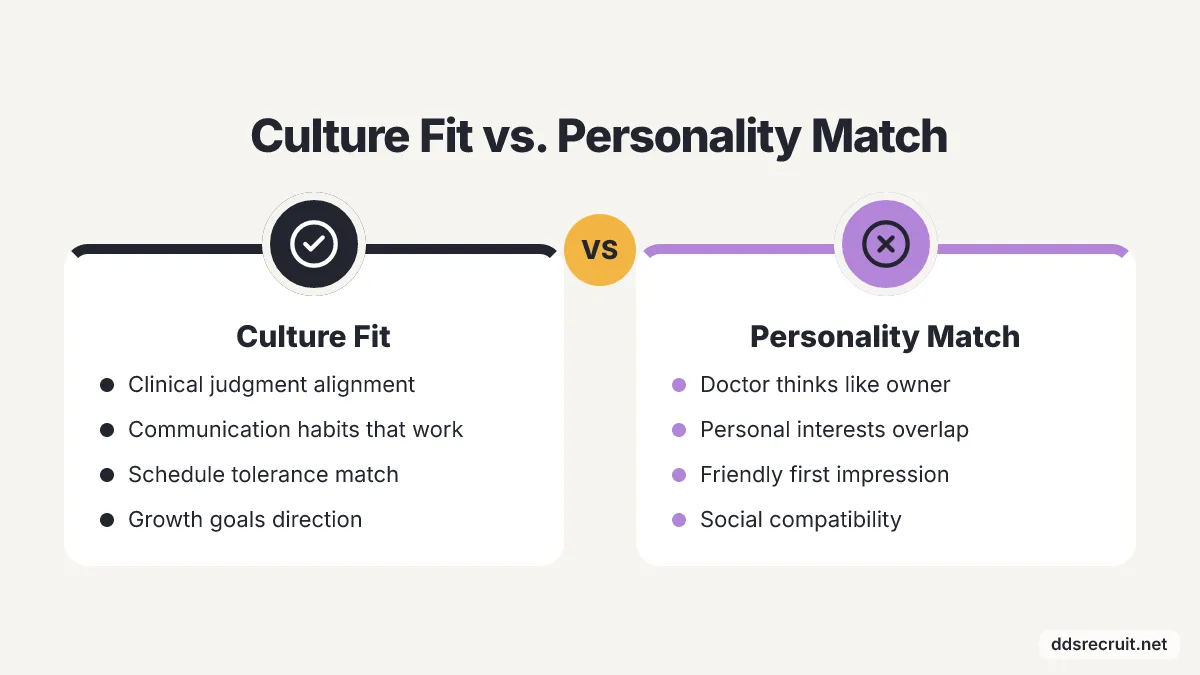
Patient pace belongs in the conversation before compensation. A dentist who wants long consults, broad autonomy, and low-volume restorative days may not fit an office built around efficient PPO flow, even if both sides like each other during the first conversation.
Clinical philosophy needs plain language. A practice should be able to say how it presents treatment, how conservative or comprehensive its diagnosis tends to be, how specialists are involved, and how much mentoring the owner expects to provide.
Team interaction deserves the same attention as clinical skill. A dentist who ignores hygiene handoffs, resists front-desk scheduling realities, or treats assistants as interchangeable labor can damage the office even while producing acceptable dentistry.
Growth expectations should be discussed before either side starts imagining a future. An associate looking for ownership, partnership, specialty exposure, or a defined leadership path needs a different conversation than a doctor who wants a stable clinical home without business responsibility.
Compensation fit has to include the model, not just the number. A dentist who has only worked in one pay structure may need a careful explanation of collections, guarantees, benefits, schedule buildout, and what success looks like after the initial start.
Geography still matters in a culture-first search. A suburban practice near a select metro may attract a different doctor profile than a rural office or a dense urban group, and the commute, family situation, and local referral patterns can shape whether enthusiasm survives the first few months.
Culture fit is measurable enough to discuss, but not so mechanical that a checklist can replace judgment. The owner, manager, and candidate need to compare real working conditions rather than rely on friendly conversation and a polished CV.
How do you assess an associate before the offer?
A bad dental hire is most preventable when the practice defines the role before evaluating the person. Culture assessment should start with the office's non-negotiables, because a vague role invites both sides to project what they want onto the same opening.
-
The practice owner should write the real reason the role exists. A replacement associate, a second-doctor growth hire, a succession planning hire, and a DSO expansion lead are different searches, even when the job title sounds similar.
-
The hiring team should name the patient experience the dentist must protect. A family-heavy PPO office, a cosmetic-driven practice, and a multi-specialty group each place different pressure on communication, diagnosis, and chairside pace.
-
The practice should separate trainable gaps from mismatch. Software familiarity, local payer knowledge, or a new scheduling rhythm can be taught, while a conflict over autonomy, ethics, patient communication, or long-term goals is harder to repair.
-
The owner should discuss decision rights before the offer. A doctor who expects full clinical independence may not thrive under a close mentoring model, while a newer associate may feel abandoned in an office that expects immediate independence.
-
The candidate should hear the hard parts of the role. A practice that hides schedule pressure, staffing instability, or transition uncertainty during hiring creates the conditions for a resignation later.
-
The final decision should include the people who will work with the dentist every day. An office manager, lead assistant, or hygiene lead may catch a communication problem that an owner misses while focusing on credentials and production.
Culture assessment is not a personality test dressed up as strategy. The practical goal is to avoid bad dental hires through culture assessment by comparing real work habits against real office conditions before either side commits.
Manual recruiting still has a place in small, relationship-rich markets. A one-chair practice with a trusted local network and no urgent vacancy may be better served by owner-led outreach first, but the trade-off is a smaller candidate pool and more owner time spent away from production and management.
Where a specialized recruiter changes the decision
A specialized recruiter is most useful when the hire affects the practice's future, not only its schedule. Associate dentists, specialists, hygienists, office managers, and senior operators each shape a different part of the business, so the search needs more context than a generic posting can carry.
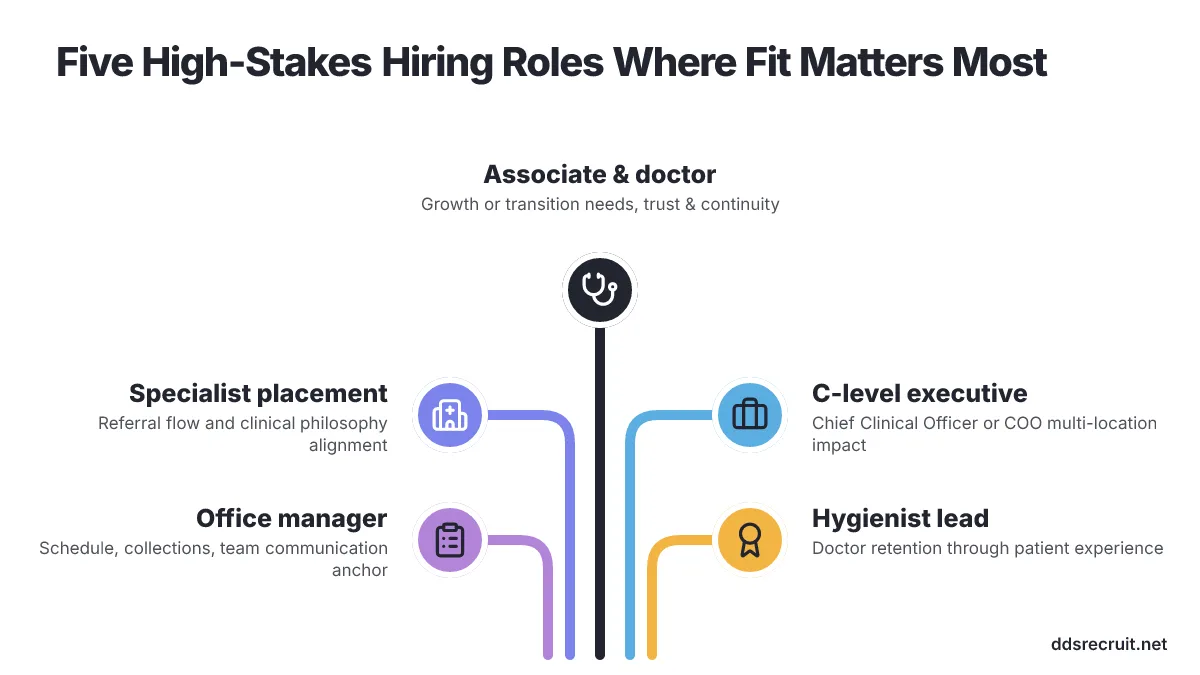
The scope matters because dental associate & doctor recruiting, specialist and in-house specialist placement, C-level executive search for a Chief Clinical Officer or COO, and DSO expansion lead placement each test fit in a different way.
Associate and doctor recruiting should connect the dentist's goals with the practice's next stage. A growth office needs a doctor who can build trust with patients and staff, while a transition-minded owner needs an associate who can carry continuity, not simply fill open chair time.
Specialist and in-house specialist placement raises the stakes around referral flow and treatment philosophy. An endodontist, orthodontist, oral surgeon, periodontist, or other specialist joining inside a practice or group must fit the clinical model and the general dentists' communication habits, not just bring a specialty credential.
C-level executive search changes the fit question again. A Chief Clinical Officer or COO in a dental group needs alignment with doctor leadership, practice operations, and growth expectations, because the wrong executive hire can affect multiple locations rather than one operatory.
Office manager and key team member hiring deserve more attention than many practices give them. The person managing schedules, collections, team communication, and patient flow can either stabilize a new dentist's arrival or magnify every mismatch, which is why a practice planning leadership support should review dental office manager recruiting before treating the role as an afterthought.
Hygienist recruiting also affects doctor retention. A new associate entering a practice with weak hygiene communication or unstable recall flow inherits a patient experience problem that may be wrongly blamed on the doctor.
DSO expansion lead placement belongs in the same culture-first conversation. A fast-growing group needs leaders who can carry the clinical and operational model into new locations without turning every new office into a different company.
A recruiter's accountability matters after the acceptance letter.
What should a long-term dental hire decide before accepting?
A dentist considering a long-term role should evaluate the practice as carefully as the practice evaluates the dentist. A strong offer can still become a poor fit when the doctor's clinical goals, lifestyle needs, or leadership ambitions point in a different direction from the office.
Clinical autonomy should be discussed in concrete terms. A candidate should ask how diagnoses are reviewed, how treatment plans are presented, when the owner expects consultation, and whether the practice wants a mentored associate or an independently operating doctor.
Schedule expectations need more than a list of days. A dentist should understand appointment lengths, new patient flow, hygiene exams, emergency slots, and how the office handles delays because those details shape stress more than the job title does.
Mentorship should be named if the dentist expects it. A newer doctor may value case review and owner access, while an experienced associate may prefer a clear lane with less oversight.
Future path deserves an honest conversation before relocation or resignation from a current role. A candidate seeking ownership, partnership, specialist exposure, or multi-location leadership should not assume those options exist unless the practice has said so plainly.
A public job post is only the start of the decision, but it helps a dentist compare location, role type, and practice direction before starting a conversation.
Practice transitions deserve extra care because the associate may become part of the owner's exit plan.
Long-term candidates should watch how the hiring conversation feels, not only what the offer says. A practice that avoids direct answers about schedule, support, leadership, or clinical expectations is asking the dentist to accept uncertainty that will not disappear after the start date.
How should a practice act before launching the search?
A practice should settle four things before it spends money on ads, talks to recruiters, or starts interviewing dentists. The search goes more smoothly when the office knows the role it is filling, the kind of doctor who can do well there, the limits it will not bend on, and who gets the final say on hiring. First, spell out the business reason for the hire. A second associate for growth, a replacement for a doctor who is leaving, a specialist addition, an office manager, and a succession planning hire each call for different candidate conversations and different signs of fit.
Second, write down the practice realities a candidate ought to hear. Patient mix, payer environment, schedule pressure, team stability, owner availability, and future opportunity should be clear enough that the right dentist can step in and the wrong dentist can walk away early. Third, decide who has to agree before an offer goes out. An owner-only choice may move faster, but a manager or lead clinical team member can spot day-to-day working conflicts before the practice commits.
Fourth, pick the recruiting path that matches the risk. A job board may be enough for a low-stakes opening with strong local demand, while a culture-first recruiting partner matters more when a failed hire would disrupt production, leadership, or a transition plan.
A practice should ask any recruiter to explain the engagement in plain terms before comparing fees, because the cheaper route can become expensive if the owner has to start the search over.
Independent recruiters also have a path into the work around dental hiring.
The next useful step is not more theory. Turn the open role into a clear fit profile before the first candidate conversation.
Conclusion
Start by writing the role the practice actually needs, not the résumé you hope to find. Name the patient base, schedule reality, clinical expectations, team dynamics, and future path before the search reaches candidates.
A culture-first hire asks for more honesty at the front end. The owner has to say what is hard about the role, the candidate has to say what kind of practice they will stay in, and the recruiter has to know dentistry well enough to keep the conversation tied to real work.
The advice stops where a practice refuses to define its own expectations. No recruiter, job board, or interview script can create long-term fit when the office has not decided what fit means.
Related reading
- How to recruit dentists who stay
- Choosing a dentistry-specialized recruiter
- Associate Doctor Placement for Practice Transition
- Decisions for Hiring the Right Dental Associate