

Finding the Right Dentist: Key Hiring Strategies
By Dr. Brian Passell and the DDS Recruit team ·

Summary: Finding the right dentist fit involves aligning a candidate's clinical skills, communication style, and career goals with the practice's specific needs. This process begins before posting a job ad by clearly defining the role, responsibilities, and team dynamics. A successful hire requires understanding the practice's culture and patient expectations, ensuring the dentist can thrive in the existing environment.
Empty operatories force practice managers into a daily shuffle of reschedules while the owner-doctor takes on extra restorative blocks to protect production. That operational drag begins long before an offer goes out, draining chair time and leaving staff scrambling to cover patient demand. The clinical team often feels pressured to endorse any licensed applicant simply to ease the immediate schedule burden.
Achieving long-term stability depends on finding the right dentist fit rather than merely collecting credentials. A dentist whose pacing, clinical scope, and communication habits run counter to the daily flow of the practice creates immediate friction with patients and staff alike. An associate who looks exceptional on paper can still destabilize an office if the actual need is an in-house specialist, an ambitious partner, or a steady doctor for routine family care.
Dental leadership teams stumble when they treat culture and clinical alignment as vague instincts during an interview. Defining fit as a series of clear operational boundaries allows an owner to evaluate candidates objectively and select a hiring channel that avoids months of wasted conversations.
Start with the role the practice can actually support
A successful recruitment campaign reflects the actual daily schedule awaiting the incoming provider rather than an idealized job description. A suburban family clinic relying on PPO insurance plans requires a clinician comfortable with steady hygiene checks, direct composite restorations, and patient trust. That daily reality contrasts sharply with an aggressive group practice adding a traveling doctor across three separate facilities.
Clinical boundaries dictate whether an associate can succeed in the first quarter. Practice owners who intend to mentor a newer clinician must honestly assess their own chairside availability, case mix, and existing referral pipelines. Clinics that genuinely need advanced surgical coverage or complex endodontics should avoid framing the position as a general associate opening, since specialized doctor placement addresses an entirely distinct clinical demand.
The scope of authority defines the working relationship from the start. A replacement provider taking over an established chart base operates under different performance targets than a pioneer doctor opening an expansion site or an executive stepping into a Chief Clinical Officer seat. Candidates expected to manage team friction, set clinical standards, or guide DSO expansion require different autonomy and compensation arrangements than an associate focused solely on operative dentistry.
Support staff readiness determines how quickly an incoming clinician reaches expected production targets. A doctor accustomed to seasoned chairside assistants and autonomous dental hygienists will experience significant distress if dropped into an office undergoing staff turnover. Outlining existing front-office scheduling systems and clinical support before contract negotiations prevents early misunderstandings about daily office friction.
Practice owners should resolve five foundational operational questions before publishing any announcement:
- Which specific procedures and chairside tasks must the incoming provider handle independently starting in month one?
- Which administrative and clinical decisions remain strictly with the practice owner, lead office administrator, or regional director?
- Which weekly schedule hours, production targets, and payer ratios govern the chairside routine?
- Which specific communication traits build immediate trust with the established patient base and auxiliary team?
- Which long-term career outcome is genuinely available, whether that means permanent associate status, equity ownership, specialist expansion, or operational leadership?
Unresolved answers to these structural questions leave an owner unable to measure true compatibility during interviews. Clarifying these baseline expectations leads directly into evaluating how candidate behavior aligns with office culture.
What does "fit" mean beyond the résumé?
What you see in daily clinical friction tells you more about candidate fit than credentials or graduation honors ever will. A résumé can confirm dental licensure, state board standings, and a completed residency, but it cannot predict how an associate deals with a delayed operatory, a child who won't cooperate, or a patient who declines a quadrant of scaling and root planing. Those small moments show up in the exchanges between the clinician, the dental assistants, and the front-office team. The clearest benchmark for mutual compatibility comes from concrete clinical moments. A busy restorative practice needs a provider who moves efficiently without sounding abrupt or dismissive during case presentations. A group practice that uses the same treatment guidelines across locations needs clinicians who accept clinical calibration. An in-house periodontist or oral surgeon has to keep talking with referring general dentists if the internal service lines are going to run smoothly.
Vague character labels do a poor job of showing whether a candidate can thrive in a specific office. Replace "compassionate team player" with clearly explains why a crown is needed to a budget-conscious patient without pressure, and the interviewer has something real to judge. Swap "natural leader" for works with the lead assistant to fix tray setups without throwing off chairside flow, and the hiring standard sits in daily reality. Practice boundaries need to be set before candidate interviews begin. A clinician who wants unrestricted material preferences and solo decision-making will clash with a multi-site group that uses standardized formularies. An early-career dentist who wants constant chairside instruction will struggle in a satellite office where the senior partner is only there two days each month.
Direct talk about daily operational problems tests candidate resilience early. Bring up tight sterilization turnarounds or complex insurance pre-authorizations, and you filter out applicants who cannot adapt to the actual work. Clinicians who stay interested after hearing those details show the practical maturity that supports long-term retention.
Patient perceptions shape the financial and clinical health of a practice. A 2015 investigation into patient priorities published on ResearchGate highlighted how care delivery and relational factors govern provider selection in a study on choosing dentists. If a clinician's chairside manner clashes with the practice's communication values, cancellation rates rise, negative reviews follow, and recall attendance drops.
Knowing which professional differences an office can live with helps keep daily team friction down. Once those cultural boundaries are set, the sourcing effort can focus on candidates who will fit that exact environment.
Where should you look for dentist candidates?
A candidate pipeline should match how hard the opening is to fill. That saves time and money. Professional referrals, public job boards, and specialized agencies each solve a different staffing problem, and each one fits a different kind of practice.
| Sourcing route | What it is best for | What it costs the practice | Where it breaks down |
|---|---|---|---|
| Personal network | Known local dentists, former residents, trusted peer referrals | Owner time and a narrower candidate pool | Confidential searches, hard-to-fill markets, or roles needing a fresh candidate base |
| Public job posting | Active candidates who are already browsing openings | Posting management and applicant follow-up | Stale responses, weak fit signals, or candidates applying broadly |
| Dental-specific recruiting | Associate, specialist, leadership, or multi-location searches where fit matters | A recruiting fee or retainer model | Searches where the owner has a known candidate and only needs a simple local introduction |
Local professional networks work best when an owner has spent years building real relationships. A senior dentist planning a practice handoff with a known regional peer is a clear case where a quiet conversation beats a broad search. Clinical standards, community standing, and personal trust are already in place in that situation.
Public career boards serve active job seekers who are already looking in a certain geographic area. A public listing falls short when a practice needs specific procedural skills or clinical fit, rather than a flood of general applicants.
Unsorted job board responses can eat up an admin team's day. Front-office staff may spend hours chasing replies, only to find compensation gaps, license transfer delays, or disagreements about the commute.
Specialized doctor placement partners fit cases where alignment matters more than raw applicant count. An entry-level associate, an established producer for a flagship location, a traveling specialist, or an executive leader each calls for industry context. Practice groups use these focused channels to find candidates with proven ability in specific procedure areas.
Recruitment services cover general associate placement, in-house specialist sourcing, and C-suite searches for positions such as Chief Operating Officer or Chief Clinical Officer. These placements tie clinical ability to organizational strategy.
Ancillary business efforts should stay separate from the doctor hiring pipeline.
The right sourcing channel comes down to the cost of leaving the role open too long. Weighing that risk helps practice owners review applicants carefully before they commit to hiring.
How do you lower the risk of a bad hire?
Hiring mistakes typically trace back to competing priorities that the practice never resolved before starting interviews. Owners frequently balance speed, clinical proficiency, compensation limits, and long-term retention goals without determining which trade-off carries the least organizational danger.
Rushing an employment offer solves immediate schedule gaps but creates substantial operational hazards. A rapid hiring decision makes sense when the candidate is personally known and possesses verified clinical competencies. Accelerating an offer becomes disastrous when desperation causes an owner to bypass vital discussions regarding daily patient volume, production pacing, or leadership philosophy.
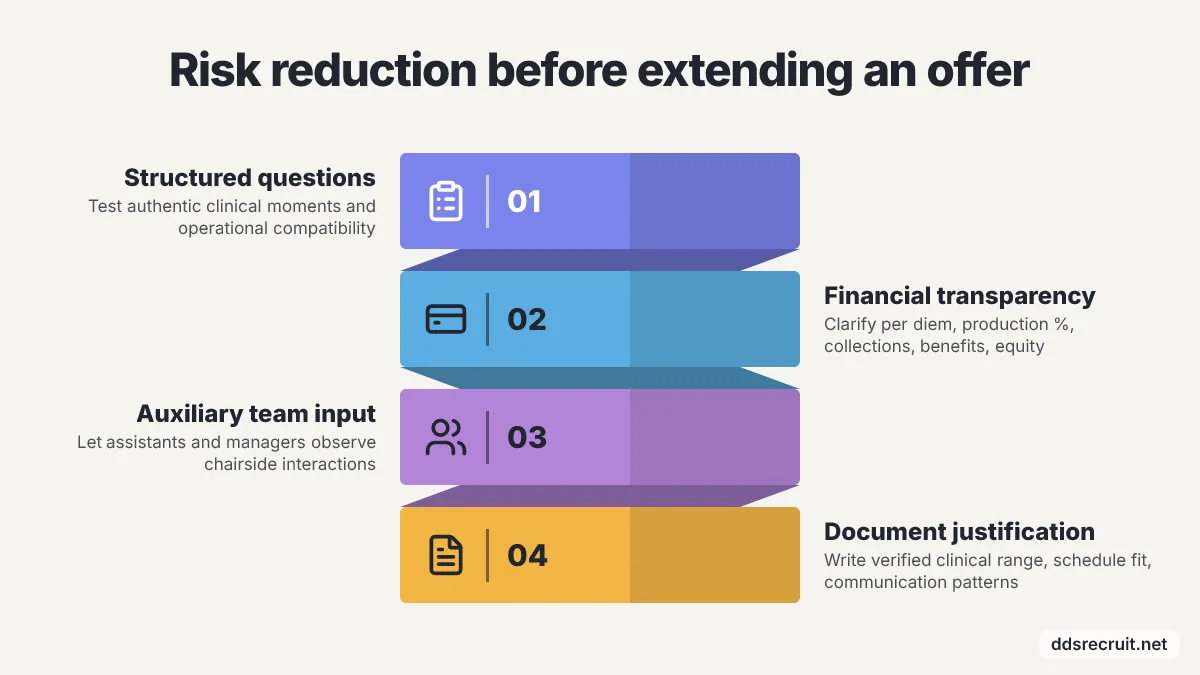
Structured interview questions test how an applicant behaves during authentic clinical moments. Asking a dentist how they navigate a restorative diagnosis with an anxious patient, how many columns they run comfortably, or which complex procedures they prefer to refer out uncovers operational compatibility. The specific answers matter less than whether those preferences match the existing systems of the office.
Financial transparency prevents mutual disillusionment late in the interview cycle. Incoming associates evaluate an opportunity across multiple metrics, including per diem guarantees, production percentages, collections policies, medical benefits, and equity options. Ambiguous compensation structures lead to early friction because dentists assess positions based on total working realities rather than verbal assurances.
Auxiliary team observations provide essential insight into daily chairside manners. Scheduling an on-site interview where the lead dental assistant and office manager interact with the candidate illuminates how the doctor handles collaboration and stress. Practice owners retain the final hiring choice, but disregarding staff feedback regarding interpersonal friction creates operational risk after onboarding.
Documenting a formal hiring justification protects practice leadership from impulse decisions. Writing down the candidate's verified clinical range, daily schedule compatibility, communication patterns, and underlying motivations exposes wishful thinking before contracts are drawn. A vague impression of likeability cannot protect chairside production or clinical morale once patient care begins.
A replacement guarantee offers financial recourse but cannot undo the clinical disruption of an empty chair. Protecting practice momentum requires validating applicant capabilities and role alignment long before extending a formal offer.
When should a recruiter handle the search?
Engaging an external search partner becomes sensible when an unfilled operatory poses strategic risk to the practice. Positions that directly drive procedural expansion, regional growth, specialist production, or clinic leadership warrant far more precision than simple administrative job postings.
Associate doctor vacancies require targeted outreach when local talent pools remain constrained or when past job advertisements produced unqualified applicants. Sourcing clinicians who possess the specific speed, chairside demeanor, and procedural capabilities required by the practice necessitates proactive recruitment across active and passive candidates.
In-house specialist additions require specialized recruitment mechanics to succeed. Integrating an endodontist, periodontist, or orthodontist into an existing general practice demands precise alignment with established referral flows, auxiliary staff setups, and patient demographics. A mismatch in procedural pacing or schedule expectations quickly stalls internal specialist productivity.
Executive leadership searches carry organization-wide consequences that demand rigorous candidate alignment. Sourcing a Chief Clinical Officer, Chief Operating Officer, or regional clinical director shapes clinical quality, compliance standards, and multi-site doctor retention. These high-level responsibilities require a targeted search that evaluates operational vision alongside clinical expertise.
Fractional recruiting arrangements provide clinics with dedicated search capacity without the overhead of an internal human resources department. This model allows practice groups to conduct targeted searches on demand without maintaining continuous departmental payroll.
Contingency or success-based search structures align financial incentives directly with hiring outcomes. Practices seeking risk-managed arrangements benefit when payment requirements attach to a verified placement rather than upfront administrative activity.
Collaborative recruiter networks expand candidate access by linking independent search specialists within a shared-fee framework. This connectivity allows dental organizations to tap into national candidate pools while working through focused industry recruiters.
Initiating an agency search early protects practice market reputation. Deploying external expertise before a public listing sits unattended for months means the practice presents an appealing, high-priority opportunity to top-tier candidates.
Build the offer around the dentist you want to keep
An employment proposal must provide clarity and reassurance rather than merely dangling attractive compensation figures. High guaranteed base salaries may generate preliminary interest, but lasting clinician retention rests on authentic alignment between daily responsibilities, practice support, and compensation mechanics.
Complete transparency regarding daily expectations forms the foundation of an effective written offer. The employment agreement should clearly specify patient demographics, expected procedural volume, assigned operatories, and performance evaluations. Outlining precisely what chairside support exists on the doctor's first day prevents the disillusionment that accompanies inflated promises.
Financial structures must reflect the authentic operational economics of the facility. An associate stepping into a PPO-heavy location evaluates their earning capacity through actual patient flow, chair time efficiency, and historical collection percentages. Specialists evaluate whether internal hygiene and doctor referrals can realistically fill their production columns, while executive candidates review operational governance and leadership autonomy.
Long-term retention begins with radical honesty during the recruitment phase. Clinicians who accept an offer based on accurate portrayals of daily clinic life have no reason to feel misled once regular patient schedules begin. Glossing over office friction or team vacancies during negotiations only compounds turnover expenses when the incoming dentist uncovers those realities firsthand.
Practice owners can validate their offer by applying a practical internal standard: if the candidate were to privately question the lead assistant about the role, would that description mirror what the owner presented? Rectifying any discrepancy between the recruitment pitch and daily office reality before sending the contract produces a stable, durable placement.
Conclusion
Draft the role brief before opening another candidate profile. Detail the required clinical procedures, auxiliary team support, daily schedule constraints, compensation parameters, and potential growth trajectory on paper, then evaluate every prospective applicant against that standard rather than schedule panic.
Securing the right clinician requires dedicated owner focus, honest auxiliary staff feedback, and a sourcing channel calibrated to the operational risk of the opening. Post publicly for routine staffing needs, rely on personal relationships when regional trust is already established, and engage specialized dental recruitment partners when confidentiality, specialist revenue, or executive scope requires precise alignment. This guidance ends once the candidate accepts the offer: long-term clinical retention rests entirely on whether the practice delivers the exact working environment it promised during recruitment.
Related reading
- Why Success-Based Recruiting Works for Dentists
- How to Recruit and Retain Dentists in 2026 Successfully
- 6 Best Ways to Recruit Dentists for DSO Growth